
Be a NURSE Your Country Needs You
Cart (0)

Female Pelvis: True Pelvis and False Pelvis | Landmarks of Female Pelvis | Diameters of Female Pelvis

Female Pelvis

Female Pelvis: True Pelvis and False Pelvis


There are 4 types of pelvis humans have.

  1. Gynecoid
  2. Android
  3. Anthropoid
  4. Platypelliod

Female pelvis are Gynecoid pelvis and the male pelvis are Android pelvis. A gynaecoid pelvis is a very good pelvis for females for childbearing and labor. The female pelvis plays a very vital role in pregnancy to give birth of a child.

Structure of Female Pelvis:

The female pelvis consists of 2 innominate bones, one sacrum and a coccyx. These innominate bones consist of a pair of ilium, a pair of ischium and a pair of the pubis.

Landmarks of Female Pelvis:

There are 9 landmarks present in the female pelvis which are listed below:
A bony structure of the maternal pelvis
Female Pelvis
  1. Sacral promontory
  2. Ala of Sacrum
  3. Sacroiliac joint
  4. Iliopectineal line
  5. Iliopubic eminence
  6. Pectineal line
  7. Pubic tubercle
  8. Pubic Crest
  9. Symphysis pubis

Landmark of Female Pelvis


Joints of Female Pelvis:


3 joints are present in the female pelvis.

  • Sacroiliac Joint
  • Sacrococcygeal Joint
  • Symphysis Pubis

Classification of Female Pelvis:

The female pelvis is divided into two parts:

Female Pelvis: False Pelvis and True pelvis

A. False Pelvis:

It is formed by the upper flared-out portion of the ilium. It protects the abdominal organs. It has no obstetrical importance.

B. True Pelvis:

The true pelvis is the bony canal through which the fetus passes during birth.

✩ The true pelvis has three parts:

True pelvis consist of inlet, cavity and outlet

Diameter of True Pelvis:

⇨ True pelvis has

  • Inlet (Brim)
  • Cavity
  • Outlet

⇨ All the diameters of the inlet, cavity and outlet are described below:

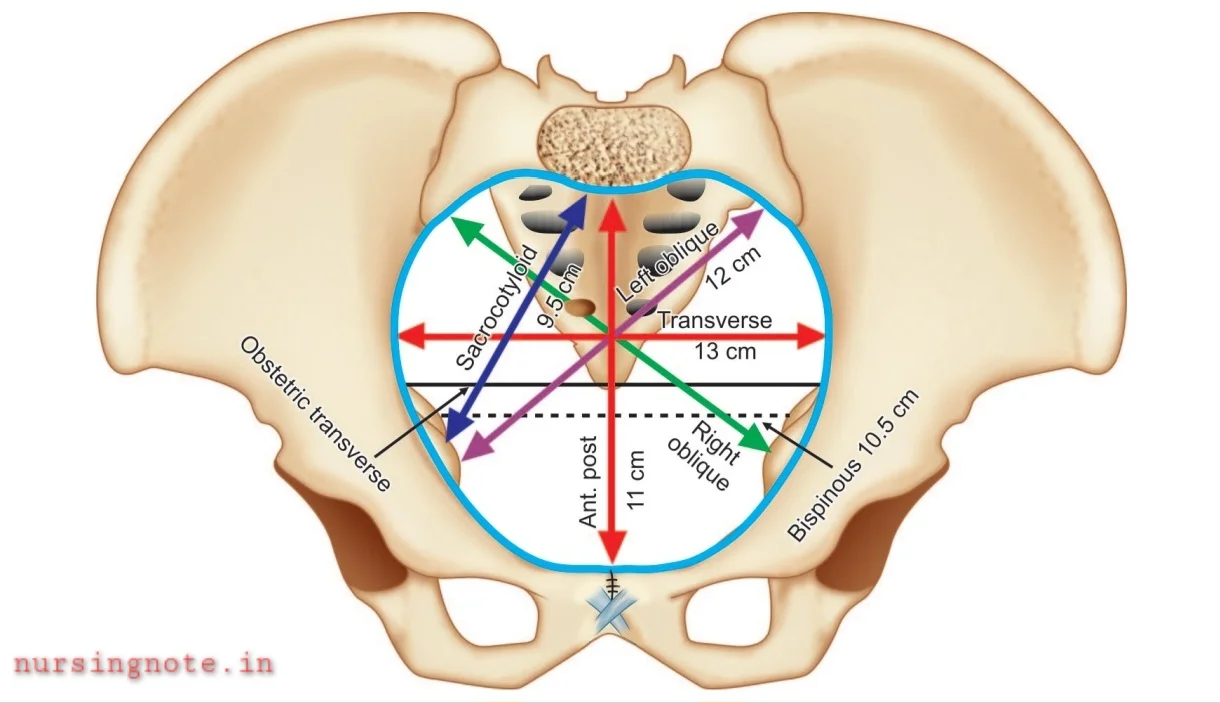
A chart of diameter of pelvis

INLET

It is formed by the sacral promontory, the iliac bones laterally and the pubic bones anteriorly
Shape: Transversely oval or Heart shape

➥Diameter of Brim or Inlet:

➢Anteroposterior Diameter(11 cm)

It is the line from the sacral promontory to the upper border of the symphysis pubis.
This diameter is of three types-
➩True Conjugate or Anatomical Conjugate
It extends from the sacral promontory to the top of the symphysis pubis.
●Its normal measurement is 11 cm or more.
➩Obstetrical conjugate
It is the distance between the midpoint of the sacral promontory to prominent bony projection in the midline of the symphysis pubis
●Its measures 10 cm
➩Diagonal Conjugate
Distance between the lower border of the symphysis pubis to the down point on the sacral promontory.
●It is 12 cm

➢Transverse Diameter(13 cm)

It is the distance between the two far ther points on the pelvic brin over the iliopectineal lines.

➢Oblique Diameter(12cm)

It starts from the sacroiliac joint to the opposite iliopubic eminence.

CAVITY

The cavity extends from the brim above to the outline below.
The shape is almost rounded
Anterior border: symphysis pubis
Posterior border: sacral hollow
Lateral border: soft tissue

➥Diameter of cavity:

Anteroposterior diameter – From the midpoint of the surface of the pubic symphysis to the junction of the 2nd and 3rd sacral vertebra.
All diameters – As there are other organs, tissue and mass present in the cavity, it is very difficult to measure other diameters. So all the diameters of the cavity are considered as 12 cm.

Anteroposterior, Transverse and Oblique Diameters of Pelvis


OUTLET

OUTLET

This outlet has greater practical significance because it includes the narrow pelvic strait through which the fetus must pass.
It is diamond-shaped.

➥Diameter of outlet:

    Obstetrical Outlet:

Anteroposterior – lower border of the symphysis pubis to tip of sacrum -11 cm
Transverse (bispinous) – between two ischial spines -10.5 cm.

    Anatomical Outlet:

Anteroposterior – lower border of ps to tip of coccyx -13 cm

Transverse (bituberous) – between 2 ischial tuberosity-11 cm.
 

Diameter Of Female Pelvis

REFERENCE: DC Dutta’s Textbook of OBSTETRICS


Write a short note on MTP Act

MTP Act (1971)

MTP Act, 1971

➢Introductions:

The Medical Termination of Pregnancy (MTP) Act, 1971, provides an overview of the legislation governing the termination of pregnancies in India. Enacted in 1971 and amended in 2002, the act aims to ensure safe and legal abortions.

Thumbnain of MTP Act India 1971

➢Objectives:

  1. The primary objective of the MTP Act is to provide a legal framework for the termination of pregnancies in a safe and medically supervised manner.
  2. Protecting Women’s Health and Rights.
  3. The MTP Act aims to prevent sex-selective abortions and discourage the practice of female foeticide.
  4. Promoting Access to Reproductive Healthcare.
  5. Maintaining Confidentiality and Privacy.
  6. The act recognizes a woman’s right to make decisions about her own reproductive health and respects her autonomy and choice in matters related to pregnancy termination.
  • Termination is performed by the medical practitioners(assisted in at least 25 MTP & degree in OBG) by the act.
  • Termination is done at the place approved under the act.
  • Termination is done for condition & within the gestation week prescribed by the act.
  • The abortion has to be reported to the director of the health service of the state.

➢When pregnancy can be terminated?

  • Continuation of pregnancy is a risk to the life of a pregnant woman or it can cause grave injury to her physical and mental health.
  • A substantial risk is that the child if born, would be seriously handicapped due to physical or mental abnormalities.
  • Pregnancy caused by rape.
  • Failure of contraceptives in married women.

➢Who can terminate the pregnancy?

➦Experience minimum 3yr who is registered in state medical register
➦6 months of house surgeon-ship in gynaecology or experience of working in the department of gynaecology –1yr
➦A Practitioner who has assisted RMP in 25 cases of Medical termination of pregnancies, at least 5 of which have been performed independently in a hospital established or maintained by the Government or a training institute approved for this purpose by the Government.

➢Required by a RMP (Registered Medical Practitioner)

➨Up to 20 wks PG Degree or Diploma in OBG

➨Completed 6 months as House Surgeon in OBG

➨At least one yr experience in dept of OBG at any hospital that has all facilities.

➢Where pregnancy can be terminated? – PLACE

  1. Hospitals established or maintained by the Government
  2. A Place approved by the Government or DLC constituted by the Government.
  1. Only the consent of women is required.
  2. If the Age is <18 yrs or a mentally ill patient, consent of a guardian is required.

Violation of The ACT:

  1. Any person doing MTP and not a RMP can be punished with rigorous imprisonment for 2-7 yrs.
  2. If terminated at a place that is not approved can be punished 2-7 yrs rigorous imprisonment.
  3. The owner of an unapproved place, performing termination can also be punished with rigorous imprisonment for 2-7 years

Psychological Changes in the First Stage of Labor

Changes in the First Stage of Labor

Psychological changes in first stage of labour:

The first stage of labor is the longest phase. This phase can take 9 hours for primigravida mothers and 5 hours for multigravida mothers.

A thumbnail of the Psychological Changes in the First Stage of Labor

✩The Changes are listed below:-

1) Cervical Dilation:

The cervix begins to open or dilate to allow the baby’s passage through the canal. This is achieved through uterine contraction.

2) Uterine Contractions:

The muscles of the uterus contract and tighten that causing the cervix to dilate. This contraction became more intense as labor progresses.

3) Rupture of the amniotic sac:

In the first stage of labor, the amniotic sac surrounding the breaks which leads to the release of amniotic fluid. This event is referred to as “water breaking”.

4) Effacement:

The cervix gradually thins out and becomes softer. It is measured in percentages.      100% Effacement = A Completely Thin Cervix5) Increase pelvic pressure:As labor progresses, pelvic pressure gets increases. A mother may feel pressure in the pelvic region.

6) Backache and cramping:

A mother will experience backaches and cramps during all the stages of pregnancy.

7) Increase vaginal discharge:

An increase in vaginal discharge may happen in the first stage. Marcus and blood often come out through the vagina.

8) Changes in vital signs:

Blood pressure, heart rate and respiration rate increase due to maternal stress.

9) Hormonal Changes:

During the first stage, a huge amount of hormonal changes, especially estrogen and progesterone level changes happen in the mother’s blood.

Write A Short Note On Partograph

partograph form

PARTOGRAPH


✯Definition of Partograph:-

A partogram or partograph is a composite graphical record of maternal and fetal data on the progress of labour on a single sheet of paper.

A thumbnail of partograph with a sample of it.

✯Inventor of Partograph:-

In, 1954 Friedman prepared the cervicography. In 1972 Philpott and Castle developed the first partograph, by utilizing Friedmar’s cervicograph, and adding the relationship of the presenting part to the maternal pelvis.
 
 
A sample copy of partograph by World Health Organization
Sample of Partograph by WHO

✯Components of Partograph:-

  1. Patient identification: Patient Name, Gravida Para, Patient ID Number, Date of Admission, Ruptured Membranes.
  2. Time: It was recorded at an interval of one hour.
  3. Fetal Heart Rate: recorded every 30 minutes.
  4. State of membranes and colour of liquor:
    ‘I’ – Intact
    ‘C’ – Clear
    ‘M’ – Meconium stained
  5. Cervical dilatation of the head.
  6. Uterine contraction.
  7. Drugs and fluids.
  8. Blood pressure at every 2 hr, and pulse at every 30 min.
  9. Oxytocin: Concentration is noted in the upper box and dose is noted in the lower box.
  10. Urine analysis.
  11. Temperature record.

✯Advantages of Partograph:-

➦ Provide important information on a single sheet of paper.
➦ Early prediction of the progress of labour.
➦ Help to prevent maternal mortality and fetal mortality.


REFERENCE: World Health Organization

Uterine Prolapse – 3rd Year GNM, Midwifery and Gynecological Nursing (Definition, Causes, Stages, Sign and Symptoms, Diagnosis,Treatment and Prevention)

Difference between normal uterus and prolapsed uterus

UTERINE PROLAPSE

🔎Definition:

Uterine prolapse is a condition where the uterus slips from its normal position and pelvic cavity into the vagina. It happens when your tissue or muscle of the uterus becomes weak.

Complete uterine prolapse, in which the uterus protrudes through the vaginal hymen is known as procidentia.

Difference between normal uterus and prolapsed uterus to understand what is Uterine prolapse

🤔Etiology/Cause:

  1. Pregnancy/childbirth with normal or complicated vaginal delivery.
  2. Weakness in the pelvic muscles due to age.
  3. Weakening tissue tone due to menopause.

⚠️Risk Factor:

  • Chronic Obstructive Pulmonary Disorder (COPD)
  • Obesity
  • Chronic cough
  • Pelvic tumours
  • Straining due to Constipation
  • Heavy lifting

🔴Using tobacco and smoking makes your lung condition bad and due to chronic cough you may leads to uterine prolapse.

𛲢Stages:

⇨First degree: The cervix drops into the vagina.

⇨Second degree: The cervix drops to the level just inside the opening of the vagina.

⇨Third degree: The cervix is outside the vagina.

⇨Fourth degree: The entire uterus is outside the vagina. This condition is also called procidentia.

🤧Signs and Symptoms/ Clinical Manifestation:

Most of the people with uterine prolapse have not experienced any signs or symptoms, but some uterine prolapse symptoms are listed below:

  • A feeling of fullness or pressure in the pelvis.
  • Pain in the pelvis or in the lower back. 
  • Pain during sex or intercourse.
  • Urination problems, Pee incontinence.
  • Constipation

If the situation goes to the level of procidentia, then symptoms may include bleeding, vaginal discharge and ulceration.

🩺Diagnostic Evaluations:

  • History collection
  • Physical examination
  • Vaginal examination, often with a speculum
  • Pelvic exam
  • Urine culture
  • Ultrasound
  • MRI

🏥Management:

⇒NON-SURGICAL MANAGEMENT:-

  1. Exercise: Pelvic Floor Muscle Training (PFMT) or Kegel exercises can help strengthen your pelvic floor muscles. This may be the only treatment needed in mild cases of uterine prolapse.
  2. Vaginal pessary: A pessary is a rubber or plastic doughnut-shaped device that fits around or under the lower part of your uterus. This device helps prop up your uterus and hold it in place.
  3. Diet and Lifestyle: Drink plenty of fluids and eat high-fibre foods, such as fruits, vegetables, beans and whole grains to avoid constipation and avoid too much heavy lifting or do that correctly.
  4. Estrogen cream: It helps in restoring the strength of vaginal tissue. Sometimes doctors may prescribe this cream to heal uterine prolapse.

⇒SURGICAL MANAGEMENT:-

  1. Hysterectomy – surgical removal of the uterus
  2. Prolapse repair without hysterectomy

🛡️Prevention:

  • Exercise regularly 
  • Avoid becoming constipation
  • Take healthy diet
  • Maintain healthy weight

GNM Previous Year Question Paper of Midwifery and Gynecological Nursing Short Question and Answer for GNM 3rd Year

Midwifery and Gynaecology Nursing Previous Year Short Question With Answer

Midwifery and Gynaecology Nursing Previous Year Short Question With Answer

Midwifery and Gynaecology Nursing Previous Year Short Question With Answer

♧Fill in the blanks:

1. The bony canal through which the fetus pass through during birth is ________

➡ Vaginal canal

2. The graphical record of cervical dilatation against duration of labor is________

➡ Partograph

3. The term placenta weighs about_______

➡ 600g

4. The name given to the lochia between 1 and 4 days is called________

➡ Lochia Rubra

5. The biparietal diameter measures about_________

➡ 9.5cm

6. The process of formation of matured ovum in the ovary is___________

➡ Oogenesis

7. The anterior fontanelle is otherwise known as________

➡ Bregma

8. The endometrium after implantation is known as________

➡ Decidua

9. Premature separation of abnormally situated placenta is called_________

➡ Abruptio placenta

10. Physiological anemia during pregnancy is the result of__________

➡ Decreased erythropoietin after the first trimesters

11. The embryotomy measures which is adopted in hydrocephalus to save the life of the mother is said_____

➡ Craniotomy.

12. Prophylactic methergine is administered after the delivery of____________

➡ Baby

13. The type of forceps which is applied when the fetal head is at pelvic outlet________

➡ Wrigleys

14. Painful menstruation is_________

➡ Dysmenorrhea

15.  _________is the name given to the endometrium during pregnancy.

➡ Gravida

16. First milk secreted from the mother is called_________

➡ Colostrum

17.  __________is the graphic representation to assess the progress of labor.

➡ Partograph

18. A dark line running from symphysis pubis to umbilicus during pregnancy is called________

➡ Linea Nigra.

19. Male gonad is__________

➡ Testes

20. Weight of a non-pregnant uterus is__________

➡ 60g

Read More: Community Health Nursing – II Previous Year Short Question With Answer

21.  ___________suture run between the two parietal bones.

➡ Sagittal

22. Posterior fontanelle is otherwise known as___________

➡ Lambdoid

23. The condition where the presentation of the fetus is constantly changing even beyond 36 weeks is________

➡ Unstable lie

24. Inability to conceive the child after regular unprotected intercourse is_________

➡ Infertility

25. Impaired involution of the uterus is called as___________

➡ Subinvolution

26. During abdominal palpation midwife can suspect polyhydramnios by feeling__________

➡ Fluid thrill

27. Brandt Andrews manoveure means___________

➡ Delivering the placenta by cord traction

28. Tenderness of calf muscle on deep pressure in deep vein thrombosis is__________

➡ Homans sign

29. Inflammation of the breast is called__________

➡ Mastitis

30. Absence of menstruation is called___________

➡ Amenorrhea.

31. Inflammation of fallopian tube is called_________

➡ Salpingitis

32. Intermittent painless uterine contractions are called_________

➡ False labor

33. The process by which the reproductive organ return to the pregravid state is called_________

➡ Involusion of uterus.

34.  ____________sign is made out by feeling increased pulsation in lateral vaginal

➡ Osiander’s

35.  __________is the first stool of the baby.

➡ Meconium

36.  _________denotes the perception of active fetal movements by pregnant women.

➡ Quickening

37. __________is the cessation of breathing for more than 20 seconds.

➡ Apnea

38. Women having their first pregnancy at or above the age of 30 years are called_______

➡ Elderly primigravida

39. _________Suture lies between the two parietal bones.

➡ Sagittal

40. The normal weight of the placenta is_________

➡ 600 grams

41.  __________is the dark line running from symphysis pubis to umbilicus during pregnancy.

➡ Linea Nigra

42. __________is the discharge from the uterus following childbirth.

➡ Lochia

43. Implantation occurs at a site other than the utrine cavity is known as____________.

➡ Ectopic pregancy

44. Brownish vaginal discharge is present during pregnancy in case of____________.

➡ Missed abortion

45. The denominator in breech presentation is__________

➡ Mentum

46. Neuromuscular harmony between the upper and lower uterine segment is called___________.

➡ Polarity

47. A women who has never given birth to a viable child is known as_________.

➡ Nullipara

48. Anterior fontanelle closes by_________.

➡ 12 Months.

49. The term used for abnormal labor________

➡ Dystocia

50. Anterior fontanel is otherwise known as___________.

➡Bregma.

51. Craving for non-nutritional substance is known as___________.

➡ Pica.

52. The denominator in face presentation is__________.

➡ Cephalic.

53. Bimanual compression is used in_________

➡ Postpartum hemorrhage

54. Fetal macrosomia is when birth weight exceeds________

➡ 4 kg.

55. Downy hair in the neonates is named as__________.

➡ Lanugo.

56. Weight of a non-pregnant uterus_________.

➡ 50-60 g

57. Planned surgical incision made on posterior wall of perineum____________.

➡ Episiotomy

58. Women in labor is called__________.

➡ Parturient

59. Fetal period begins from___________.

➡ 8th Week.

60. Inability of the new-born to initiate the breach is ______________

➡ Dystocia

61. Excessive vomiting in early pregnancy is known as ______________

➡ Hyperemesis gravidarum

62. The normal length of umbilical cord is _______________

➡ 50 CM

63. The average duration of third stage of labour in primigravida mother is _________________

➡ 10 – 15 minutes

Postpartum Psychosis – 3rd Year GNM, Midwifery and Gynecological Nursing (Definition, Signs and Symptoms,Causes, Diagnosis, Treatment)

A woman with postpartum psychosis holding a baby in her arms.

 POSTPARTUM PSYCHOSIS 

⇒DEFINITION:- 

Postpartum Psychosis is an acute mental disorder or a psychotic reaction occurring following childbirth or abortion. 

🔴Postnatal psychosis or puerperal psychosis is a psychological emergency. 

A woman with postpartum psychosis holding a baby in her arms.
Postpartum Psychosis

⇒CLINICAL MANIFESTATION:-

  1. Hallucinations – sensing falls, visions, smells or sounds which is not really present.
  2. Delusions – It is basically a false belief
  3. Mood changes such as mania or depression 
  4. Depersonalization (some people describe this as an out of body experience) 
  5. Disorganized thinking or behaviours
  6. Insomnia – It is a sleeping disorder in this you may find yourself very hard to stay asleep
  7. Self-harming – Women with this postpartum psychosis have this type of intention to harm themself. She might commit suicide or may try to kill their child.

⇒ETIOLOGY:-

  1. History of Mental Illness – If the patient has any past history of other mental illness.
  2. Schizophrenia 
  3. Bipolar Disorder
  4. Number of pregnancies
  5. family history of mental health condition – If any other family members have any kind of psychotic disorder then the pregnant mother also has a chance to get this mental problem.
  6. Sleep deprivation
  7. Hormone changes – hormonal disbalances due to pregnancy can also be the causes of postpartum psychosis.
  8. Other medical conditions
  9. Post pregnancy stress can affect mothers mental health

⇒Diagnostic Evaluation:-

  • History Collection
  • Physical Examination
  • Blood Test
  • Urine and other body fluid test
  • Mental Status Examination Test
  • Imaging Tests

                ⇾CT Scan
                ⇾MRI

⇒Treatment:-

▲Medication

Antipsychotic

Mood stabilizers

Antiseizure drug

Lithium

▲Electroconvulsive Therapy (ECT)

It is the therapy in which electrical shock is provided to the patient in a very low amount and for very short time only.

⬛ With these proper nursing care is very important to totally cure the mental health problems.

NursingNote.IN

NursingNote is a trusted platform for GNM & Nursing students, providing exam-oriented notes, PDFs, question papers, and career guidance to help you succeed confidently.

Quick Links

Legal
